

Nadeem Tanoli
The technology that helped identify SARS-CoV-2 in late 2019 is now being used beyond the pandemic to change the way difficult infections are diagnosed and monitored.
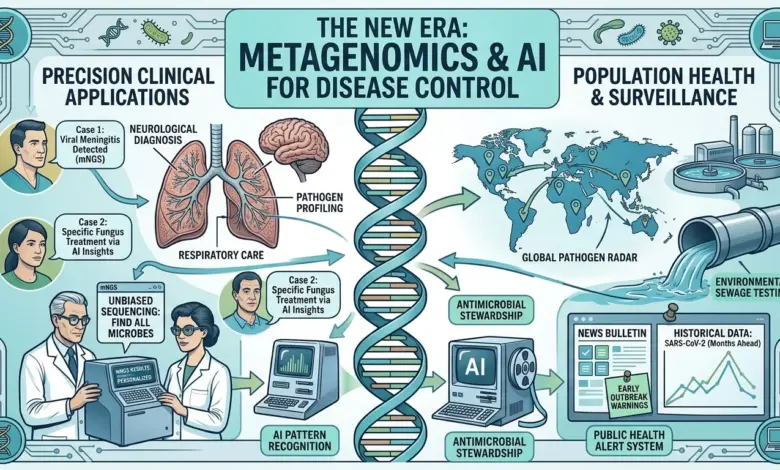
Metagenomic next-generation sequencing, known as mNGS, is an unbiased method that sequences nearly all genetic material in a sample. Combined with artificial intelligence, it is moving from research laboratories into intensive-care units, specialist hospitals and national surveillance systems.
The approach marks a shift from testing for a suspected pathogen one by one to detecting almost any known or novel microbe. It can also help interpret the patient’s own immune response, allowing doctors to assess which findings are clinically important.
In neurological emergencies, the stakes are high. Patients may arrive with fever, confusion, headache or weakness, and conditions such as meningitis or encephalitis may be caused by a virus, bacterium, fungus or an autoimmune attack on the brain or spinal cord. The treatments differ sharply: antimicrobials are used for infection, while immune-suppressing medicines are used for autoimmune disease. Conventional tests often come back negative, leaving doctors with little time and limited certainty.
Metagenomic sequencing of cerebrospinal fluid has shown particular value in such cases. Long-term data from the University of California, San Francisco clinical laboratory, covering nearly 5,000 samples over seven years, found that mNGS detected organisms in about 14 per cent of cases. It also identified infections missed by standard testing in roughly one-fifth of confirmed central-nervous-system infections.
Earlier prospective work showed that mNGS alone diagnosed about 22 per cent of infections and influenced treatment decisions in a meaningful proportion of those cases. Reported real-world examples include the detection of hepatitis E virus in a patient who had previously been thought to need a liver transplant, and the identification of tuberculosis that had been mistaken for lung cancer and had nearly led to major surgery.
Respiratory and critical-care settings are also seeing benefits. At Great Ormond Street Hospital, same-day pan-microbial metagenomics for children in intensive care changed clinical management in nearly 30 per cent of samples. It influenced antibiotic decisions in about a quarter of cases and found dozens of organisms missed by routine tests.
Broader reviews of prospective studies show the strongest impact in critically ill patients with lower-respiratory-tract infections, central-nervous-system disease and sepsis. These are the situations where traditional diagnostics often leave the largest gaps.
For immunocompromised patients, including transplant recipients, cancer patients and those on immunosuppressive therapy, the gains may be especially important. Ordinary infections can quickly become life-threatening, and hundreds of possible pathogens make sequential testing slow and incomplete. Metagenomics offers a single-test net that can detect bacteria, viruses, fungi and parasites together, saving valuable time.
A major challenge, however, is that raw metagenomic data can be difficult to interpret. Human DNA dominates many samples. Common colonisers and laboratory contaminants often appear. A detected microbe is not always the cause of illness. Earlier versions of the technology could take days or even a week to return results.
Newer sequencers can now produce data within hours. Artificial intelligence and machine-learning models speed up the remaining steps by removing host sequences, classifying organisms, recognising highly divergent or novel microbes, identifying antimicrobial-resistance genes and ranking which detections are most likely to be causing disease.
Some systems also study host gene expression, examining what proteins the patient’s cells are producing. This can help distinguish an active immune response to a pathogen from colonisation or contamination. The added host-response layer supports more individualised treatment rather than treating every organism that appears in a report.
The combined use of mNGS and AI is also supporting antimicrobial stewardship. It can help doctors reduce unnecessary broad-spectrum drugs when no pathogen is found, or escalate treatment more precisely when an unexpected organism is detected.
The same technology has public-health value. Sequencing data generated during patient care can feed surveillance systems. In the United Kingdom, the mSCAPE programme links anonymised metagenomic results from NHS respiratory networks with national health-security systems, creating a real-time pathogen monitoring system. Results that once took days can now guide clinicians in about six hours while also updating surveillance databases for novel or rising threats.
Wastewater and environmental metagenomics extend this monitoring further. Studies of sewage from dozens of cities across continents have mapped urban viromes, detected early signals of circulating viruses and, in some historical cases, identified SARS-CoV-2 genetic material months before the first clinical diagnoses. Similar approaches are being studied for other pathogens and for antimicrobial-resistance genes circulating in communities.
When clinical and environmental data are combined with AI pattern recognition, the possibility of earlier outbreak detection increases substantially.
Adoption is growing. Hospitals in the United Kingdom, the United States and elsewhere are incorporating rapid respiratory and neurological metagenomics into care pathways. Commercial assays capable of detecting more than a thousand bloodstream pathogens from cell-free DNA are entering markets. Regulatory interest is also rising, with some platforms receiving breakthrough-device designations.
Important barriers remain. Cost and turnaround time still restrict routine first-line use in many settings. Incidental findings, where microbes are present but not responsible for illness, require careful clinical interpretation and clear reporting standards. Regulatory systems designed for targeted tests do not always fit unbiased sequencing, creating challenges for market authorisation and reimbursement.
Standardisation of laboratory methods, bioinformatics pipelines and quality measures is still incomplete. Equity is another concern, as high-resource centres are currently gaining the greatest benefit, while lower-resource regions with heavier infectious-disease burdens may fall behind without investment in accessible platforms and training.
Ethical issues are also emerging. Questions remain over whether every incidental microbe should be reported and how clinicians should respond when a pathogen is detected but no specific treatment exists. Clear guidelines, drawing on lessons from human genomics, will be needed as the technology expands.
Metagenomics combined with AI is more than an improved diagnostic test. It represents a new approach to infectious-disease medicine. Instead of asking only whether a particular pathogen is present, doctors can increasingly ask what is present, whether it is causing harm and what response is best for the patient and the wider population.
The COVID-19 pandemic demonstrated the value of rapid, unbiased pathogen discovery. Since then, the same tools have been refined to improve care for meningitis, pneumonia, sepsis and unexplained fever, while strengthening systems meant to warn societies of future outbreaks.
The technology is still developing. Costs need to fall, interpretation must become more automated and standardised, and access must widen. But the direction is clear: infectious-disease care is moving away from reactive, pathogen-by-pathogen testing towards a more precise, comprehensive and proactive model. Patients with the most complex infections are already seeing the benefits, and the wider public-health impact is beginning to take shape.




